























































This article was originally published by The Daily Yonder.
In the quiet corners of rural Minnesota, a silent health crisis is unfolding. While medical advancements have pushed lung cancer survival rates to historic highs when caught early, a significant portion of the population remains outside the reach of these life-saving diagnostic tools. A groundbreaking research project spearheaded by the University of Minnesota’s Masonic Cancer Center is now attempting to bridge this divide, transforming the way rural clinics approach patient care and cancer detection.
The Core Objective: A Shift in Clinical Culture
At the heart of the initiative is a simple, yet profound, shift in medical practice: moving lung cancer screening from an optional, patient-led task to a proactive, team-based clinical standard. Dr. Abbie Begnaud, a pulmonologist and associate professor at the University of Minnesota Medical School, is leading the charge alongside the Minnesota Cancer Clinical Trials Network.
The project posits that the key to increasing screening rates lies within the rural doctor’s office. By empowering the entire clinic staff—from front-desk receptionists to nursing teams and primary care providers—to identify, educate, and schedule patients, researchers hope to dismantle the systemic barriers that have long kept rural residents from accessing essential imaging.
"Anybody with lungs can get lung cancer," Dr. Begnaud explains. "When found early, lung cancer survival rates can reach 80% to 90%. The problem is that less than 20% of eligible Minnesotans are actually screened for lung cancer. We are leaving too many people behind."
The Anatomy of a Health Disparity
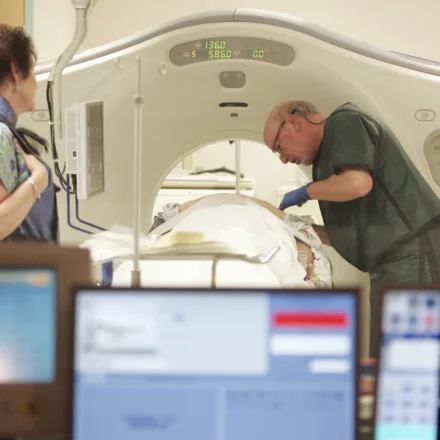
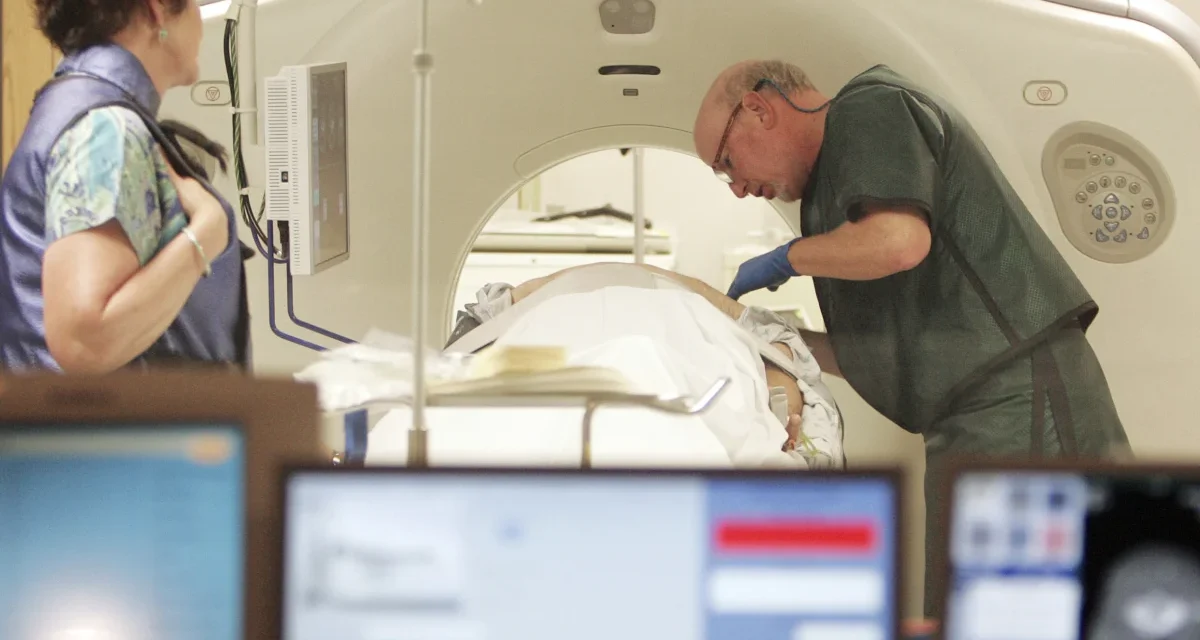
The disparity between urban and rural health outcomes is well-documented, but the specific challenges surrounding lung cancer are multifaceted. Current clinical guidelines recommend annual low-dose computed tomography (LDCT) scans for adults aged 50 to 80 who have a significant history of heavy smoking.
The Rural Smoking Paradox
Data from the U.S. Surgeon General’s 2024 report highlights a stark reality: rural adults are significantly more likely to smoke than their urban counterparts—15.4% compared to 10.1%. Furthermore, these individuals often smoke at higher intensities, averaging 15 or more cigarettes per day, and face steeper hurdles when attempting to quit.
The Weight of Stigma
Beyond physical and geographic obstacles, there is a pervasive psychological barrier: shame. Decades of public health messaging, while successful in reducing overall smoking rates, have inadvertently created a culture of stigma around tobacco use. Patients who smoke often internalize this blame, leading to a reluctance to engage with the healthcare system for fear of judgment.
"It’s really important to get people to be open to screening to try to decouple the kind of shame or blame that goes along with smoking," says Dr. Begnaud. "People who have smoked or continue to smoke are certainly aware that it’s bad for their health, and they know that everyone else is thinking about it. They internalize these messages of blame."
Chronology of the Pilot Program
The road to this current initiative began with a pilot program aimed at testing the feasibility of a "whole-of-office" approach to screening.
Phase 1: Identifying the Bottlenecks
Researchers first observed the patient journey within six primary care clinics in rural Minnesota. They identified that the standard procedure—handing a patient a brochure and asking them to schedule their own scan at a distant imaging center—was a primary point of failure. The process required patients to navigate a complex administrative system, often while managing limited transportation options or work schedules.
Phase 2: Implementing the "Whole-of-Office" Strategy
During the pilot, clinic staff were trained to act as navigators. The process was redesigned to:
- Systematic Identification: Staff used electronic health record triggers to identify patients eligible for screening based on age and smoking history.
- Integrated Education: Rather than just handing out pamphlets, the team engaged in direct, non-judgmental conversations about the benefits of screening.
- Point-of-Care Scheduling: Instead of sending patients home to make a phone call, staff worked to schedule the screening appointment immediately, often while the patient was still in the examination room.
Phase 3: Measuring Initial Success
The results were promising. The pilot clinics saw a 30% increase in the number of screening orders for eligible patients. While the small sample size precludes a definitive claim that the approach will solve the rural screening deficit entirely, it provided the "proof of concept" necessary to justify a larger, statewide trial.
Supporting Data: The Landscape of Risk
The urgency of this project is supported by broad, national statistics that underscore the need for targeted intervention. According to the American Lung Association, while national smoking rates are at historic lows, the geographic distribution of tobacco use remains uneven.
Regional Vulnerabilities
The Surgeon General’s report identifies the Midwest and Southeast as regions where rural adults are 40% more likely to smoke than those in the Northeast or West. These areas also suffer from higher rates of tobacco-related diseases and, crucially, lower "quit ratios." This means that not only are people starting to smoke at younger ages in these regions, but they are also finding it harder to stop, leading to a higher long-term risk profile that necessitates aggressive screening programs.
The Impact of Access
In rural settings, the "distance to care" is not just a measurement of miles, but a measurement of risk. When a patient has to travel hours to an imaging center, the likelihood of completing a screening drops precipitously. The University of Minnesota’s approach aims to mitigate this by integrating the administrative burden into the primary care visit, ensuring that the logistical barrier does not become a life-threatening delay.
Official Responses and Clinical Perspectives
The medical community has responded with cautious optimism. Public health experts have long argued that screening is the most underutilized tool in the fight against lung cancer, particularly for high-risk populations.
"What we really wanted to see was: Is this approach feasible? Is this doable in clinics?" Dr. Begnaud noted. "And largely, the answer to that is ‘yes.’ The clinic teams were excited to learn more and work on this project."
However, experts emphasize that this is not a panacea. The integration of screening into primary care must be paired with smoking cessation support and an empathetic approach to patient care. The goal is to move from a punitive model of "warning" patients about the dangers of smoking to a supportive model of "protecting" patients from the consequences of their habits.
Implications: A Path Forward
The implications of this research extend far beyond Minnesota. If the statewide trial proves that the "whole-of-office" model can be scaled, it could provide a blueprint for rural health systems across the United States.
Expanding the Scope
The next phase of the project involves expanding to a larger number of rural clinics. This expansion will seek to gather more robust data on long-term outcomes—specifically, whether the increase in screening orders translates to a higher rate of early-stage cancer detection.
The Moral Imperative
For Dr. Begnaud, the motivation remains personal and deeply rooted in her clinical experience. "Every time I see somebody who comes to me who should have been screened and wasn’t, and now they have a stage 3 or a stage 4 lung cancer, it motivates me to get up and work harder tomorrow," she says. "There’s still a lot of work to do."
Future Challenges
The success of this program will depend on several factors:
- Infrastructure: Continued investment in rural imaging capabilities.
- Staffing: Addressing the burnout and resource constraints often faced by rural clinic staff.
- Education: Continuing to shift the narrative from one of shame to one of empowerment.
As the University of Minnesota continues to gather data, the project stands as a testament to the power of systemic change. By simplifying the path to screening, the research team is not only addressing a diagnostic gap but is also affirming the value of rural lives, ensuring that regardless of geography or history, every patient has the chance for early intervention and a better prognosis.
The journey to eradicate the disparity in lung cancer outcomes is long, but for the residents of rural Minnesota, the path has become significantly clearer. With each appointment scheduled and each patient reached, the project moves one step closer to ensuring that the most lethal cancer in the country is no longer a death sentence.